Prostate cancer is the most common cancer in Black men, accounting for 44% of all new cancer diagnoses among them. According to the American Cancer Society, Black men are diagnosed with prostate cancer at a rate 67% higher than White men, and they are more than twice as likely to die from it.
That second number is the one that should stop us. A 67% higher diagnosis rate does not explain a death rate that is twice as high. Something else is going on: cancers found later, cancers that behave more aggressively, and care that does not reach Black men the same way.
Meanwhile, the problem is getting worse for all men. The American Cancer Society reports that late-stage prostate cancer diagnoses have been rising 4.6% to 4.8% per year. Cancer found late is much harder to cure.
The fix starts with a conversation, and for Black men it needs to happen earlier than most of us were taught.
Why the risk is higher: ancestry, family and genes
African ancestry. Some of the inherited risk for prostate cancer is concentrated in men of African descent. The best-known example is a region of chromosome 8 called 8q24, which contains multiple variants that raise prostate cancer risk in Black men. One rare 8q24 variant found in men of African ancestry has been linked to prostate cancer clustering in families, earlier diagnosis and more aggressive disease.
Family history. A father, brother or son with prostate cancer raises a man’s risk, especially if that relative was diagnosed before age 65. The American Cancer Society treats this as seriously as race: men with one close relative diagnosed before 65 should start the screening conversation at 40. Family history also includes women. Breast, ovarian and pancreatic cancer in close relatives can point to inherited genes that also cause prostate cancer.
Specific genes. A large 2026 study of more than 12,000 men of African ancestry in seven countries found that inherited mutations in five genes, ATM, BRCA2, CHEK2, HOXB13 and PALB2, raised the risk of aggressive prostate cancer two- to six-fold. These mutations were found in about 4% of men with aggressive or metastatic disease. BRCA2, the same gene linked to breast cancer, is among the most important.
The same study showed how much individual risk varies. Combining a man’s mutation status, his polygenic risk score (a measure of many small genetic effects) and his family history, lifetime risk of prostate cancer ranged from 3% to 74%. Men with all three risk factors had 34 times the risk of metastatic prostate cancer. That is the case for precision medicine in one sentence: two Black men of the same age can have very different risks, and we can now begin to tell them apart.
PSA screening: what the guidelines say
The PSA test is a simple blood test that measures prostate-specific antigen, a protein made by the prostate. A rising or elevated PSA can be the first sign of cancer, often years before any symptoms. Major organizations disagree about when Black men should start:
| Organization | When to start the conversation for Black men | Notes |
|---|---|---|
| Prostate Cancer Foundation (2024) | Baseline PSA at age 40 to 45 | Annual screening strongly considered, depending on PSA level and health |
| American Cancer Society | Age 45 | Age 40 with more than one close relative diagnosed before 65 |
| U.S. Preventive Services Task Force (2018) | Age 55 to 69, an individual decision | No separate recommendation for Black men; an update is in progress |
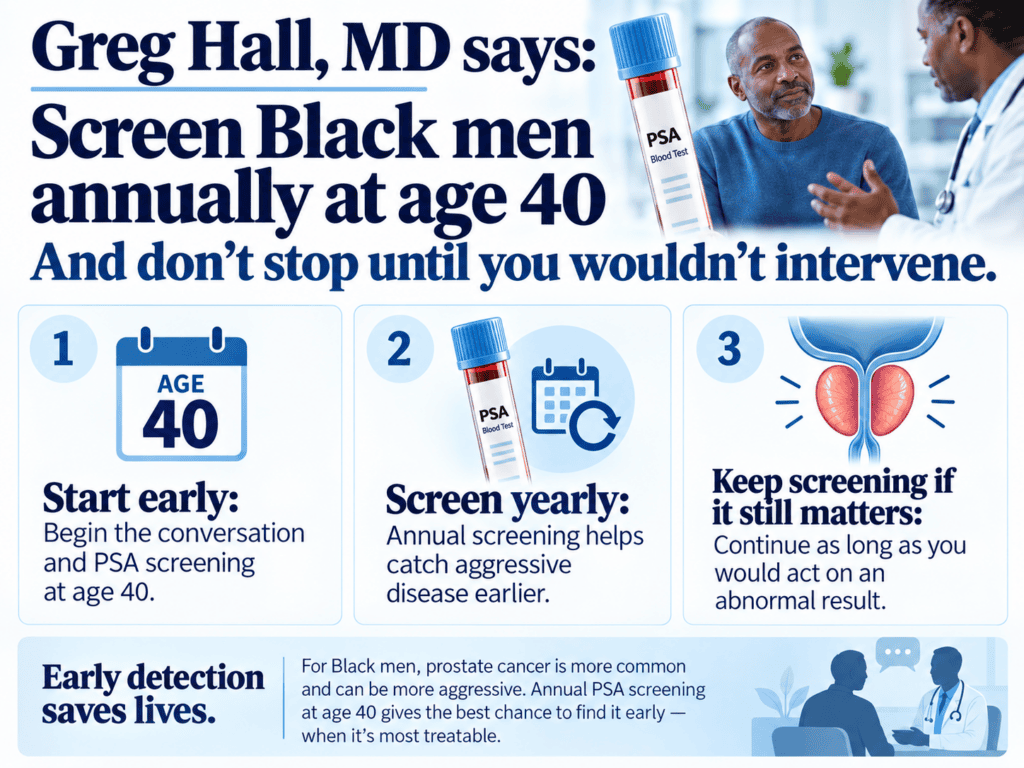
The Task Force (USPTF) acknowledges that Black men carry a heavier burden of prostate cancer but concluded there was not enough evidence for a separate recommendation. That aspect makes no sense… higher risk, more advanced disease, yet no separate recommendation. That is partly because the large screening trials enrolled few Black men. Is that our fault? Black men are more often diagnosed younger and at a more advanced stage, so waiting until 55 can mean missing the years when the cancer is most curable. Simply bad advice!!
The Prostate Cancer Foundation guideline, published in NEJM Evidence, was written specifically for Black men. In my view it is the right starting point: a baseline PSA at 40, with the frequency of follow-up tests guided by the result, but usually annually. A low baseline PSA is reassuring and could justify less frequent testing, but i still check them annualy. A higher one tells us who needs closer watching.
The balance has also shifted. Today, many men with low-risk cancer are offered active surveillance, careful monitoring instead of immediate surgery or radiation. An MRI before biopsy can help avoid unnecessary procedures. These advances reduce the harms of screening, which makes the case for earlier testing stronger.
A good screening conversation for a Black man should cover:
- His personal risk, including race, family history on both sides and any known genetic mutations
- What a baseline PSA can tell him, and what happens if it is elevated
- The option of active surveillance if a low-risk cancer is found
- How often to repeat the test based on his results
Here is the most hopeful finding in prostate cancer research. When Black and White men receive the same care, their outcomes look much more alike.
A 2019 study in JAMA Oncology followed more than 306,000 men, including nearly 55,000 Black men, in the Veterans Affairs health system and four clinical trials, where access to care was equal. In these settings, Black and White men had comparable rates of death from prostate cancer. In the clinical trials, Black men actually did better.
The same researchers pointed to what drives the gap in the general population: lower PSA screening rates, later-stage diagnoses, less insurance coverage, and higher rates of obesity and diabetes that affect which treatments men receive and whether they complete them.
Treatment disparities, and what equal care can do
That does not mean biology plays no role. Black men carry more of certain high-risk inherited variants, and researchers continue to study differences in how their tumors behave. But it does mean that a large share of the death gap can be closed with care we already know how to give: earlier detection, timely treatment and follow-through.
The precision medicine connection
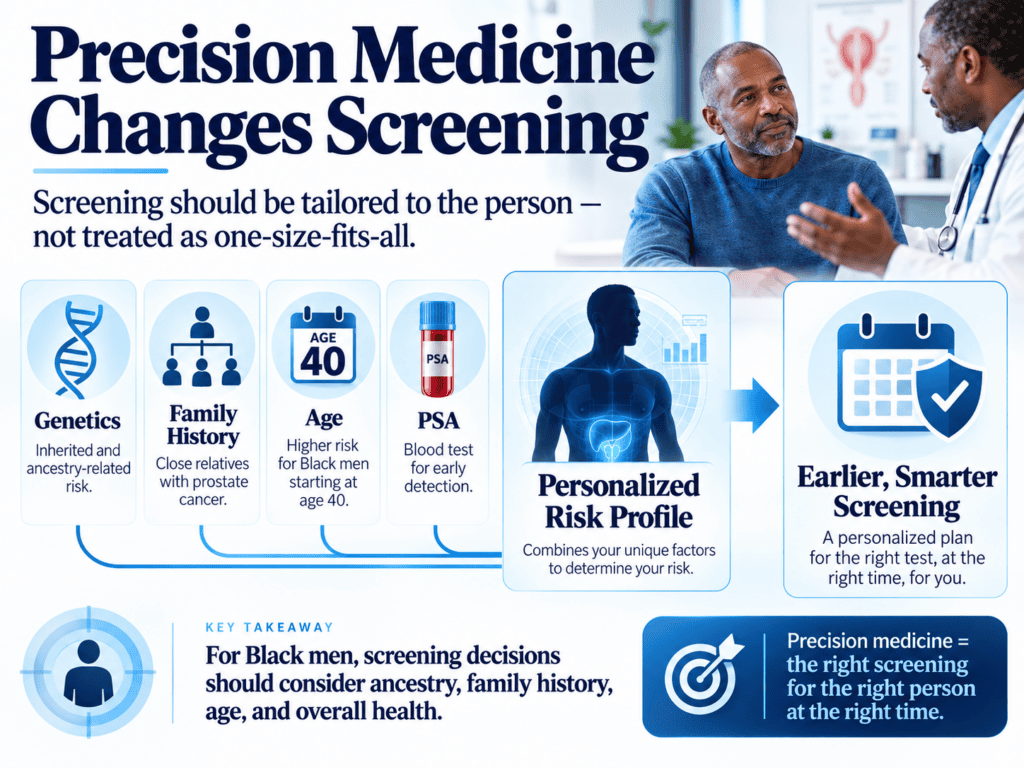
Precision medicine means care matched to the individual, not the average. For prostate cancer in Black men, it works in layers:
- Race starts the conversation. Being a Black man is a reason to begin screening discussions at 40. It is a trigger to look, not a diagnosis.
- Family history sharpens the picture. Prostate, breast, ovarian and pancreatic cancer in close relatives, on either the father’s or the mother’s side, move a man into a higher-risk group.
- A baseline PSA measures the man in front of you. One number in his early 40s sorts men who can be tested less often from those who need closer follow-up.
- Genetic testing finds the highest-risk men. Inherited mutations in genes such as BRCA2 change screening, and if cancer is found, they change treatment. Men with prostate cancer and certain mutations may qualify for targeted drugs called PARP inhibitors. National guidelines recommend genetic testing for men with high-risk or metastatic prostate cancer and for those with a strong family history.
- Polygenic risk scores are coming. Researchers are building scores that work in men of African ancestry, who were left out of earlier genetic studies. Combined with family history and mutation testing, these scores can separate a man with a 3% lifetime risk from one with a 74% risk.
- Know what can change your PSA. Finasteride and dutasteride, common pills for an enlarged prostate or hair loss, lower PSA by about half, so the result should be doubled before it is judged. Ejaculation, long bike rides and prostate infections can raise PSA for a few days. Tell your doctor about these before you are tested, and repeat an unexpected result before moving to a biopsy.
This is the approach I describe throughout Precision Medicine for African Americans. Race is where the question starts. Testing is where the answer comes from. Ignoring race means Black men lose the early conversation they need. Stopping at race means missing the differences among Black men themselves.
What Black men and their families should do
- Start the conversation by 40. Ask your doctor for a baseline PSA. Do not wait for symptoms; early prostate cancer usually has none.
- Learn your family history, on both sides. Ask about prostate, breast, ovarian and pancreatic cancer, and the ages when relatives were diagnosed. If your father or brother had prostate cancer, tell your doctor and consider starting at 40.
- Ask about genetic testing if you have a strong family history or a relative with a known BRCA or other cancer gene mutation.
- Know your numbers. Keep track of your PSA results over time. A steady rise matters, even within the “normal” range.
- If you are diagnosed, ask about all your options, including active surveillance for low-risk cancer, genetic testing of your cancer and clinical trials.
- Skip vitamin E supplements. In the large SELECT trial, men taking 400 IU of vitamin E daily had a 17% higher risk of prostate cancer. Be cautious with high-dose calcium supplements as well; get calcium from food and talk with your doctor about how much you need. I explain the dairy and calcium research in Lactose Intolerance in African Americans.
- Women, start the conversation at home. Wives, daughters and sisters are often the reason men get screened. Ask the men you love whether they have had a PSA test.
Black men have the highest risk of dying from prostate cancer in this country, but that risk is not destiny. When Black men are screened, diagnosed and treated on time, their outcomes improve dramatically. The conversation just needs to start earlier.
Sources
- American Cancer Society. Cancer Statistics for African American and Black People, 2025. February 2025.
- American Cancer Society. 2025 Prostate Cancer Statistics Report.
- American Cancer Society. Cancer Screening Guidelines by Age.
- Garraway IP, et al. Prostate Cancer Foundation Screening Guidelines for Black Men in the United States. NEJM Evidence. 2024. See also the Prostate Cancer Foundation summary.
- U.S. Preventive Services Task Force. Prostate Cancer: Screening. 2018; update in progress.
- Gong J, et al. Genetic and biological drivers of prostate cancer disparities in Black men. Nat Rev Urol. 2024;21:274-289.
- Chen F, Haiman CA, et al. Integrating Pathogenic Variants, Polygenic Risk Score, and Family History for Prostate Cancer Risk Estimation in Men of African Ancestry. Eur Urol. 2026;89(5):416-425.
- Dess RT, et al. Association of Black race with prostate cancer–specific and other-cause mortality. JAMA Oncol. 2019. Study; news summary.
- Fred Hutch. SELECT data shows vitamin E increases prostate cancer risk. 2011.
- Hall GL. Precision Medicine for African Americans. 2nd ed. Springer; 2025.