Getting breast cancer less, but dying from it more
Black women get breast cancer slightly less often than white women, yet they die from it at a much higher rate. How is that? This is a “classic” health disparity: less cancer, but more deaths. According to the American Cancer Society, Black women have a 38% higher breast cancer death rate than white women, despite a 5% lower rate of getting the disease. Black women are also less likely to be diagnosed while the cancer is still small and localized (58% vs 68%).
A Southwest Oncology Group study of nearly 20,000 patients in cancer clinical trials found that African American patients with breast, ovarian, and prostate cancer had worse survival even when they received the same stage-matched treatment and follow-up. That does not mean we are powerless to change these results, because we are not. Falling smoking rates have already helped narrow the gap in lung cancer deaths in the Black community. And we’re not done.
More mammograms find cancer earlier
For breast cancer, studies show that mammography, chemotherapy, and hormone therapy (when indicated) all lower the risk of death. In short, if we use the prevention and treatment tools available, we can save and extend lives. Black women should make a point of getting mammograms starting at age 40. The American College of Radiology recommends yearly mammograms from 40, and the US Preventive Services Task Force recommends them at least every two years from 40 to 74. A mammogram flattens the breast to take an x-ray, and the radiologist looks closely for small changes from your prior mammogram. The real value of mammograms is comparing this year’s image to last year’s “normal” one. Never wait to feel a lump to get tested. Mammograms find problems much earlier than you could feel them. That’s why breast exams are not nearly as valuable as a mammogram.
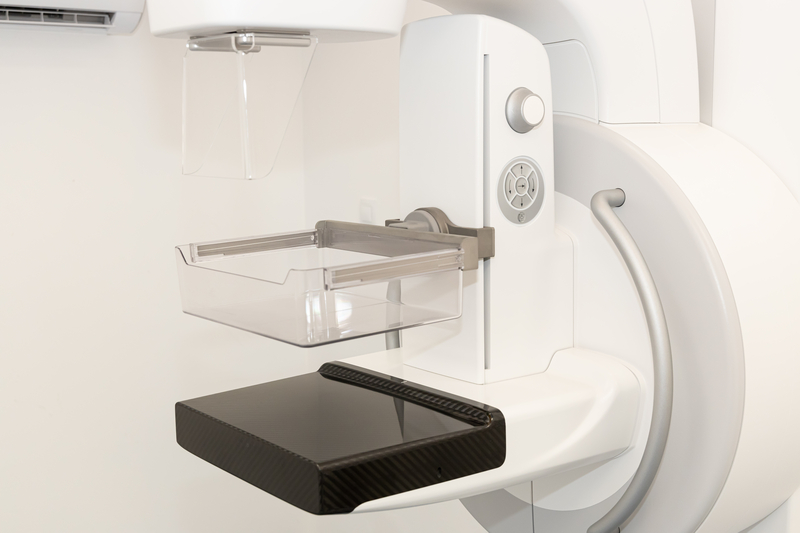
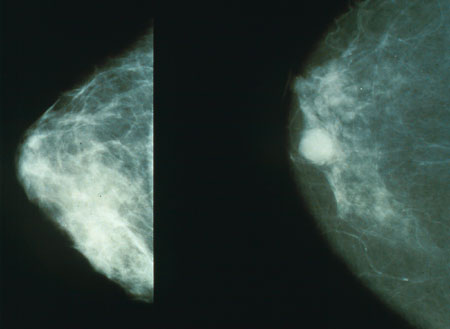
Flattening the breast does not cause cancer to spread (as some knuckleheads have said), and it causes no harm. The radiation dose is very small, and the benefit far outweighs the risk.
Fat cells fuel cancer cells
Excess weight raises the risk of dying from breast cancer, and given the higher rates of obesity in Black women, it may explain part of the poorer outcomes we see. Research suggests that fat cells can supply energy to cancer cells and cause inflammation that weakens the immune system. Weight matters most after menopause, when excess body fat raises breast cancer risk. Reaching a healthy weight is one of the best steps you can take to lower your risk of breast cancer and of the cancer spreading.
Does breast size matter?
Being overweight and having dense breasts both increase your risk of breast cancer. “Dense” means more glandular and fibrous tissue on the mammogram, not breasts that feel firm, and your mammogram report will tell you if your breasts are dense. Overall breast size, however, does not appear to raise your risk.
Exercise helps
Regular physical activity lowers the risk of breast cancer, according to many studies. By getting more exercise, Black women can lower their risk. Try walking every day and aim for 7,500 steps or more. Watch the video below for the full message.
Mammograms have changed everything
Many of my patients complain about mammograms. They don’t like the brief squeeze of their breasts, which is understandable. But the benefit of that moment of discomfort is huge. Nothing beats finding cancer early! The smaller the cancer, the easier it is to treat. That’s why doctors spend less time doing breast exams and more time ordering mammograms. Mammograms can “see” tumors while they are still too small to feel. Removing them is easier, and the surgery leaves a much smaller scar.
The precision medicine connection
Breast cancer is not one disease, and Black women are not a single risk group. Precision medicine uses your biology, genes, and history to guide screening and treatment. Here is how it applies to Black women.
1. Know your tumor type
Black women are about twice as likely as white women to have triple-negative breast cancer, a type that grows faster, often strikes younger women, and doesn’t respond to hormone therapy. Black women also have lower survival than white women for every subtype and stage except localized disease. If you are diagnosed, ask what your tumor’s ER, PR, and HER2 status is, because it decides your treatment.
2. Get your risk assessed by 25
The American College of Radiology now recommends that all women, and Black women in particular, have a breast cancer risk assessment by age 25 to see if screening should start before 40. Black women carry BRCA1 and BRCA2 mutations at rates similar to white women, but they are less likely to be offered genetic testing. If close relatives had breast, ovarian, prostate, or pancreatic cancer, ask about genetic counseling.
3. Ask whether your test results fit you
The Oncotype DX 21-gene test helps decide who needs chemotherapy for early hormone-positive breast cancer. A 2021 JAMA Oncology study found that Black women had higher breast cancer death rates than white women within the same score category, and the test predicted outcomes less accurately for them. Your score is still useful, but discuss it with your oncologist in light of your full picture.
4. Know the safety limits of your genes
About two-thirds of Black Americans have the Duffy-null blood type, which naturally lowers neutrophil (white blood cell) counts without raising infection risk. Those normal-for-you counts can lead to unnecessary chemotherapy delays, dose cuts, or exclusion from clinical trials. Ask your oncologist whether Duffy status testing applies to you. Another gene, DPYD, controls how the body clears capecitabine and 5-FU chemotherapy. The Y186C variant, found almost only in people of African ancestry, cuts that enzyme’s activity by about half and can cause severe toxicity. Ask about DPYD testing before starting these drugs.
To learn more, patients and families can read Better Black Health, and clinicians can see Precision Medicine for African Americans.